Indications
Treatment of rheumatoid arthritis and osteoarthritis.
Treatment of acute gout attack.
Management of pain in the following conditions: Pain due to problems with spine (such as ankylosing spondylitis, back pain).
Acute musculoskeletal disorders Injuries (sprains and strains).
Primary dysmenorrhea.
Post – operation pain.
Contraindications
- Hypersensitivity to ketoprofen or any other ingredients in this medicine.
- Patients who have experienced asthma, urticaria, or allergic-type reactions induced by aspirin or other NSAIDs.
- Pregnant women in the third trimester of pregnancy.
- Active peptic ulcer.
- Children under 15 years old.
- Severe heart failure
- Severe hepatic insufficiency
- Severe renal insufficiency
- Peri-operative pain in the setting of coronary artery bypass graft (CABG) surgery.
Dosage and administration
- For pain, inflammation, acute musculoskeletal disorders: 50 - 100 mg, 2 – 3 times/day.
- For primary dysmenorrhea: 50 mg, up to 3 times per day if needed.
- For renal and hepatic impairment patients: a reduce dose of 33 - 50% compare to normal.
- Mild renal impairment: maximum 150 mg/day.
- Moderate renal impairment: maximum 100 mg/day.
- Impaired hepatic function and serum albumin concentration < 3.5 g/dL: 100 mg/day.
Do not use over 300 mg ketoprofen per day. Drug should be taken within or after meals.
Precaution
Undesirable effects may be minimised by using the lowest effective dose for the shortest duration necessary to control symptoms.
Ketoprofen should not be used to treat pain related to discreetly bleeding (pain after accident) or pain related to injuries in the nervous system as risk of bleeding.
Cardiovascular, Renal and Hepatic impairment:
At the start of treatment, renal function must be carefully monitored in patients with heart failure, liver dysfunction, cirrhosis and nephrosis, in patients receiving diuretic therapy, in patients with chronic renal impairment, particularly if the patient is elderly. In these patients, administration of ketoprofen may induce a reduction in renal blood flow caused by prostaglandin inhibition and lead to renal decomposition.
NSAIDs have also been reported to cause nephrotoxicity in various forms and this can lead to interstitial nephritis, nephrotic syndrome and renal failure.
In patients with abnormal liver function tests or with a history of liver disease, transaminase levels should be evaluated periodically, particularly during long-term therapy. Rare cases of jaundice and hepatitis have been described with ketoprofen.
Cardiovascular and cerebrovascular effects
Appropriate monitoring and advice are required for patients with a history of hypertension and/or mild to moderate congestive heart failure as fluid retention and oedema have been reported in association with NSAID therapy.
Clinical trial and epidemiological data suggest that use of some NSAIDs (particularly at high doses and in long-term treatment) may be associated with a small increased risk of arterial thrombotic events (for example myocardial infarction or stroke). There are insufficient data to exclude such a risk for ketoprofen.
Patients with uncontrolled hypertension, congestive heart failure, established ischaemic heart disease, peripheral arterial disease, and/or cerebrovascular disease should only be treated with ketoprofen after careful consideration. Similar consideration should be made before initiating long-term treatment in patients with risk factors for cardiovascular disease (e.g. hypertension, hyperlipidaemia, diabetes mellitus, smoking).
Respiratory disorders:
Patients with asthma combined with chronic rhinitis, chronic sinusitis, and/or nasal polyposis have a higher risk of allergy to aspirin and/or NSAIDs than the rest of the population. Administration of this medicinal product can cause asthma attacks or bronchospasm, particularly in subjects allergic to aspirin or NSAIDs.
Gastrointestinal bleeding, ulceration and perforation:
GI bleeding, ulceration or perforation, which can be fatal, has been reported with all NSAIDs at any time during treatment, with or without warning symptoms or a previous history of serious GI events.
Some epidemiological evidence suggests that ketoprofen may be associated with a high risk of serious gastrointestinal toxicity, relative to some other NSAIDs, especially at high doses.
The risk of GI bleeding, ulceration or perforation is higher with increasing NSAlD doses, in patients with a history of ulcer, particularly if complicated with haemorrhage or perforation, and in the elderly. Elderly patients should commence treatment on the lowest dose available. Combination therapy with protective agents (e.g. misoprostol or proton pump inhibitors) should be considered for these patients, and also for patients requiring concomitant low dose aspirin, or other drugs likely to increase gastrointestinal risk. Ketoprofen should not be used in patients with any history of peptic ulceration.
NSAIDs should be given with care to patients with a history of gastrointestinal disease (e.g. ulcerative colitis, Crohn's disease) as these conditions may be exacerbated.
Patients with a history of gastrointestinal toxicity, particularly when elderly, should report any unusual abdominal symptoms (especially GI bleeding), particularly in the initial stages of treatment.
Caution should be advised in patients receiving concomitant medications which could increase the risk of ulceration or bleeding, such as oral corticosteroids, or anticoagulants such as warfarin, selective serotonin-reuptake inhibitors or anti-platelet agents such as aspirin.
When GI bleeding or ulceration occurs in patients receiving ketoprofen, the treatment should be withdrawn.
Pediatric use
Safety and effectiveness in pediatric patients have not been established.
Geriatric use
As with any NSAIDs, caution should be exercised in treating the elderly (65 years and older).
Storage
Store at temperature below 30°C, protect from light.

Emla 5% (5g)
Tadalafil Stella 10mg (2 tablets/box)

Dipozag 30mg (4 tablets/box)
Restasis 0.05% (30 single-use vials/box)
Oscal Agi 0.6g (30 sachets/box)
Elofarvita (3 blisters x 10 tablets/box)

Benzac Power Patch (12 patches/box)
Benzac Blackhead Control Facial Scrub (60g)
E-ScarPatch 5cm x 7cm (8 pcs/bag)
Ozzotin Sleep Expert (10 tablets/box)
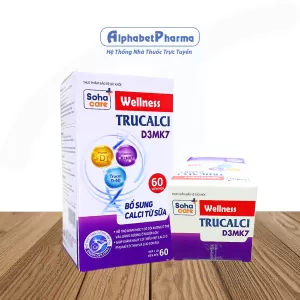
Trucalci D3MK7 Wellness (60 tablets/box)
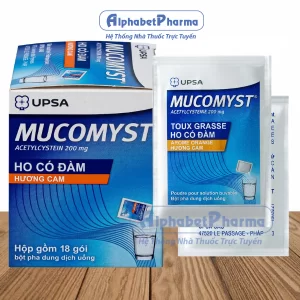
Mucomyst 200mg (18 sachets/box)

Alvityl Appetite Syrup Pineapple Flavour (100ml)

Cerave Blemish Control Cleanser (236ml)

Cetaphil Baby Wash & Shampoo With Organic Calendula (400ml)

Cetaphil Pro AD Derma Instant Relief và Moisturising Gel (59ml)

Cetaphil Pro Ad Derma Skin Restoring Moisturizer (295ml)

Benzac Purifying Cleanser (130ml)

Cetaphil Sun Kids Liposomal lotion SPF50+ (150ml)

Omega 3-6-9 Alaska Propharm (100 softgels/box)

Benzac AC gel 2.5% (30g)
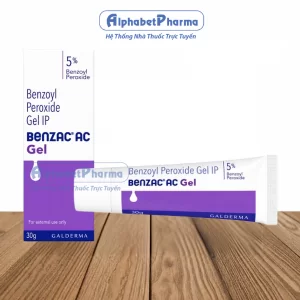
Benzac AC gel 5% (30g)
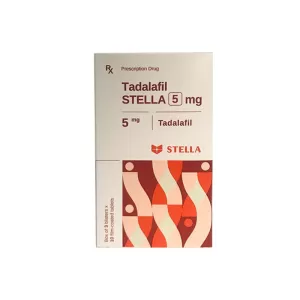
Tadalafil Stella 5mg (3 blisters x 10 tablets/box)

SOSLac G3 (15g)

Cetaphil Baby Gentle Wash & Shampoo (230ml)
Naturen Z (10 blisters x 10 capsules/box)

Raid Lemon Orange (600ml)


Vitamin 3B PV (10 blisters x 10 softgels/box)

Viên dầu gấc PV (100 softgels/box)

Javel Bleach AXO (400ml)

Liverton 140mg (10 blisters x 10 capsules/box)

Pamidstad 2.5mg (2 blisters x 30 tablets/box)
NNO Vite Aplicapz (3 blisters x 10 softgels/box)

Liverbil OPC (5 blisters x 10 capsules/box)

VG-5 Danapha (4 blisters x 10 tablets/box)

NNO Regenexx (30 softgels/box)

Cloderm cream (15g)
Beprosone Cream (15g)

Calcium Hasan 500mg (20 effervescent tablets/tube)
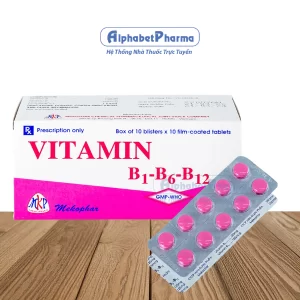
Vitamin B1-B6-B12 MKP (10 blisters x 10 tablets/box)
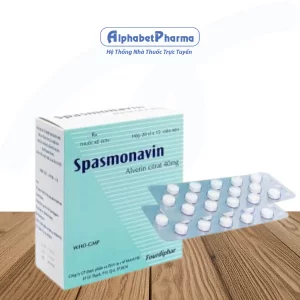
Spasmonavin 40mg (20 blisters x 15 tablets/box)
TanaMisolblue (10 blisters x 10 tablets/box)
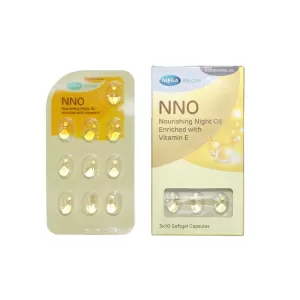
NNO Nourishing Night Oil (3 blisters x 10 softgels/box)
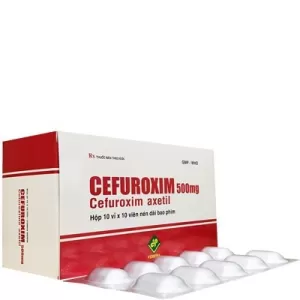
Cefuroxim 500mg Vidipha (10 blisters X 10 tablets/box)

Acetylcystein 200mg Vidipha (20 blisters x 10 capsules/box)
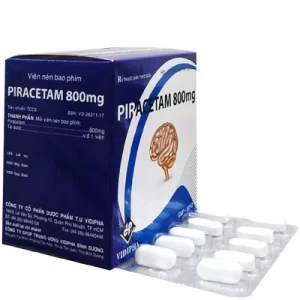
Piracetam 800mg Vidipha (10 blisters x 10 tablets/box)
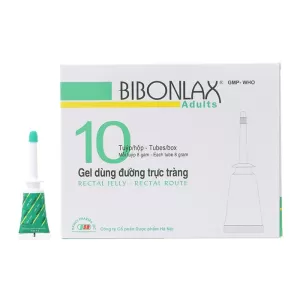
Bibonlax Adults 8g (10 tubes/box)

Beroxib 200mg Enlie (3 blisters x 10 capsules/box)
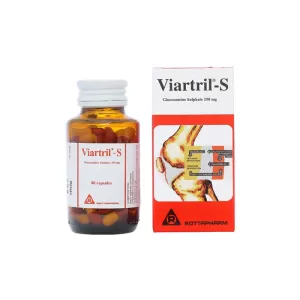
Viartril - S 250mg (80 capsules/box)

Sucrate Gel (30 sachets/box)
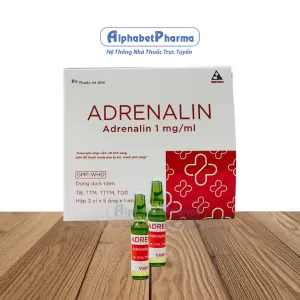
Adrenalin 1mg/1ml (2 blisters x 5 ampoules/box)

Liquid balm Kim Linh (6ml)

Unikids Zinc (50g)
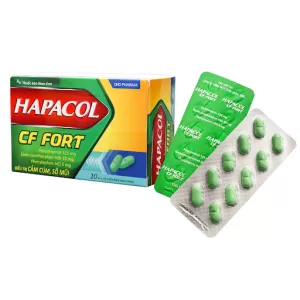
Hapacol CF Fort (10 blisters x 10 tablets/box)

Panangin (50 tablets/box)

Venpoten (30 capsules/box)

Dạ dày Nhất Nhất (2 blisters x 10 tablets/box)
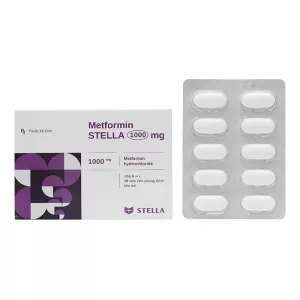
Metformin Stella 1000mg (6 blisters x 10 tablets/box)

Yumangel (20 sachets/box)
Rosuvastatin Stella 20mg (3 blisters x 10 tablets/box)

Eugica syrup (100ml)
Panadol Cold Flu (15 blisters x 12 tablets/box)


Special Kid Immunite (125ml)
Verospiron 50mg (3 blisters x 10 capsules/box)


Ceelin (120ml)

Clinical Thermometer Lilika
Cefimbrano 200 (10 tablets/box)

Natriclorid 0.9% Vĩnh Phúc (1710ml)

Salonpas Liniment (50ml)
Salonpas (12 pads/box)
Methionine 250mg MKP (100 capsules/box)

Gofen 400mg (5 blisters x 10 softgel capsules/box)

Tiger Balm White (30g)

Giao Co Lam Extra Kingphar (60 capsules/box)

Cetampir plus (3 blisters x 10 tablets/box)

Irbesartan Stella 150mg (2 blisters x 14 tablets/box)